
ACL Injury and Reconstruction
The anterior cruciate ligament (ACL) is an important stabilizer of the knee against translational and rotational forces. The ACL connects the femur (thigh bone) to the tibia (shin bone) and crosses through the central portion of the knee.
The ACL is most commonly injured in recreational or high-level athletics. Since the ACL stabilizes against rotation and translation of the knee, if the force on the knee exceeds the strength of the ACL then the ligament will tear. The most common situation for this injury is a non-contact, pivot injury such as changing direction in soccer or football or landing awkwardly after jumping in basketball or volleyball. Additionally, any sport that twists the knee can cause injury to the ACL like skiing, wrestling, or martial arts. Patients who tear their ACL typically feel a pop in the knee followed by rapid and significant swelling and stiffness. For various reasons, females are much more likely to sustain an ACL tear in athletics than males.
In the athletic, young patient population, ACL tears are typically treated with surgery to restore stability to the knee and allow for return to cutting and pivoting activities. With ACL reconstruction surgery our goal is to stabilize the knee, provide normal motion, and prevent meniscus and cartilage injury to allow patients to return to their previous level of activity.

On this page I have many videos that do a deep dive into the ACL injury as well as surgical treatment. Through these videos I hope to educate my patients regarding their injury, surgery, and recovery.
Video Education
Dr. Merritt has developed an in-depth video series on ACL injury, surgical options, and recovery. These videos help patients understand the condition, the procedure, and what to expect.

Treatment Options
ACL tears in athletic patients are treated surgically. The most common treatment is what is called an “ACL Reconstruction” where the damaged ligament is removed and replaced with a new ligament that we call a graft. The graft can be taken from another part of the body or, in some circumstances, from a cadaver.
In certain types of ACL tears, a repair can be done in which the torn tissue is left in the knee, sutured back in place, and allowed to heal. While there are some advantages to this technique, there are also many situations where a repair is not possible or not recommended. Please see my ACL Repair page here to learn more.
In some older patients, the ACL tear is treated without surgery and the knee rehab is done with physical therapy.
What is ACL Reconstruction?
An ACL reconstruction is a surgery that replaces a torn anterior cruciate ligament with a new piece of tissue, called a graft, which heals into the bone and takes over the job of the original ligament. It is called a reconstruction rather than a repair because a torn ACL usually cannot simply be stitched back together. The ligament tears in the middle of the joint, where it has a poor blood supply, and the tissue is stretched and frayed rather than cleanly cut. Sewing it back together rarely holds. So instead of repairing the old ligament, I build a new one.
The surgery is done arthroscopically, through several small incisions around the knee. A camera goes in through one incision and the instruments through the others, so I can see the entire inside of the joint on a screen. The first step is to look at everything: the ACL, the menisci, the cartilage surfaces, and the other ligaments. Then I clean out the torn remnants of the old ACL and drill a small tunnel in the femur (thigh bone) and another in the tibia (shin bone), placed exactly where the original ligament attached. The graft is passed through those tunnels and fixed at both ends with buttons or screws so it sits in the same position and at the same tension as a native ACL.
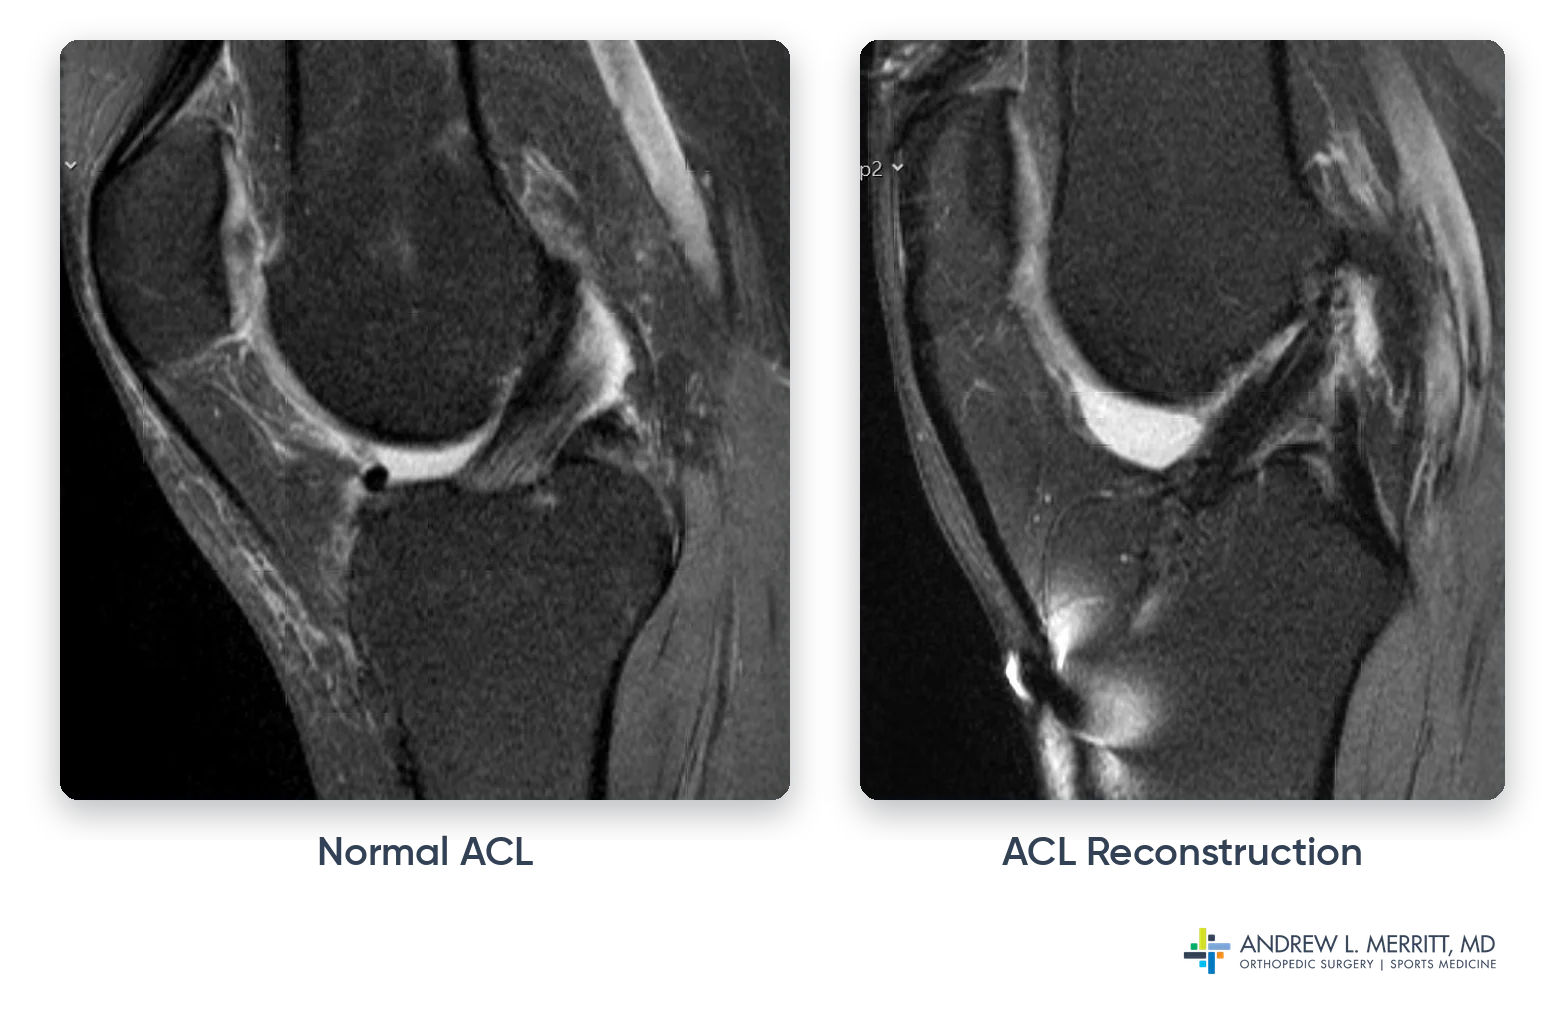
The graft is a piece of tendon, and this is the most important thing to understand about the recovery. On the day of surgery it is a strong, mechanically secure structure held in place by hardware. Over the following months it goes through a biological transformation: the tunnels heal around it, blood vessels grow into it, and nerve fibers return. It slowly turns from a piece of tendon into a living ligament. That process is what takes the better part of a year, and it is why the timeline for returning to cutting and pivoting sports is measured in months, not weeks, even when the knee feels good early on.
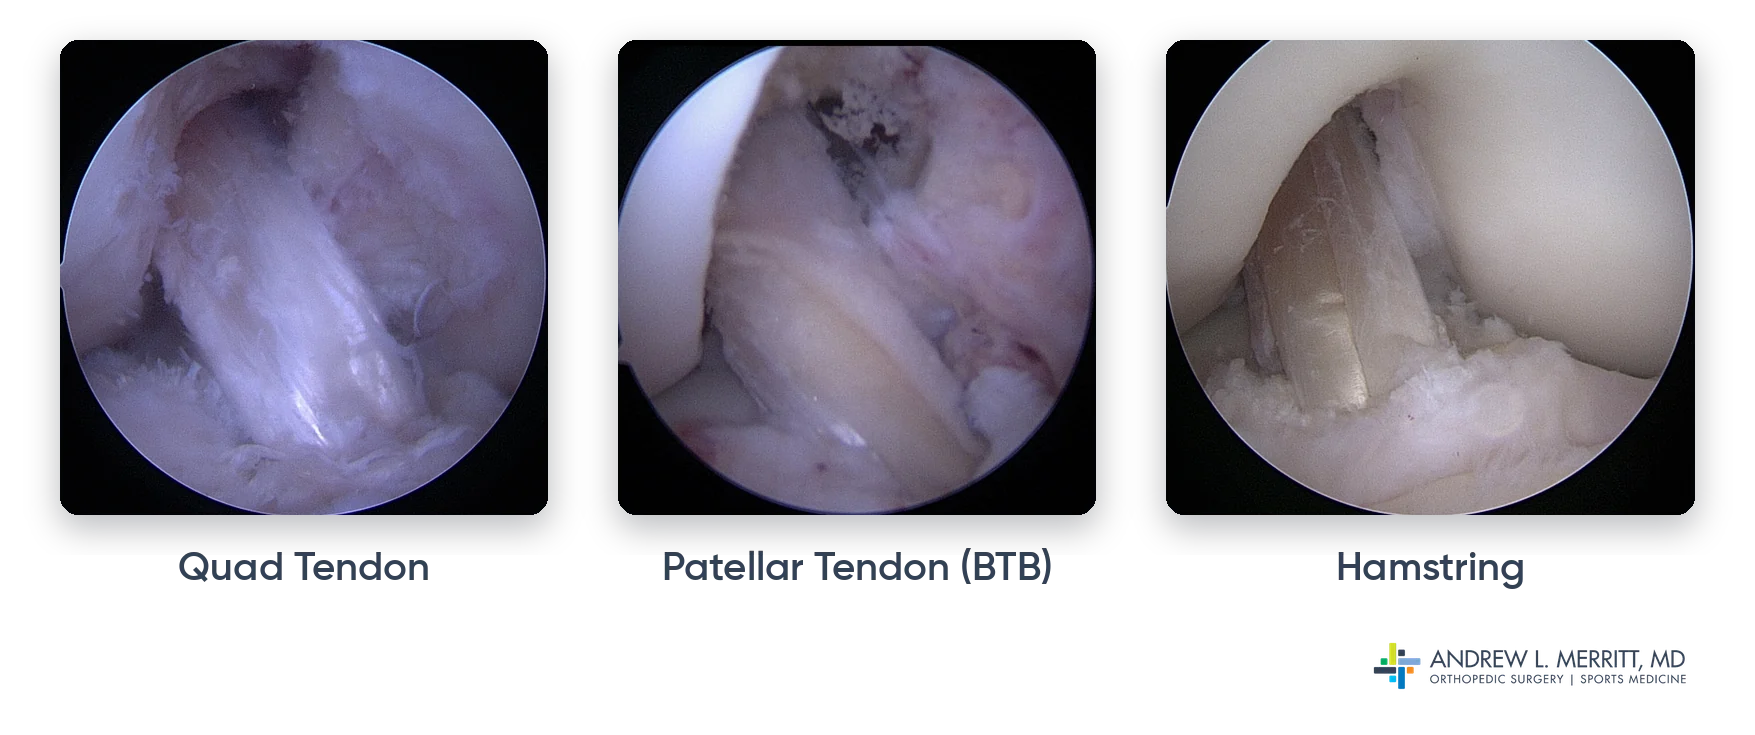
There are several graft options, and I customize the choice to your injury, anatomy, activity level, and goals. In most patients I use an autograft, meaning tissue taken from your own body during the same surgery. The common choices are the quadriceps tendon, the patellar tendon, and the hamstring tendons. Autografts heal faster and have a lower re-tear rate than allografts, which are donor tissue from a tissue bank. Allografts still have a role, particularly in older or lower-demand patients, and we will go through the options together at your clinic visit so you understand the tradeoffs. I discuss more about grafts in the videos above.
An ACL reconstruction is often combined with additional treatments of the knee. The same twisting injury that tears the ACL often tears the meniscus or damages the cartilage, and I address those problems during the same surgery. In patients at higher risk of re-tearing the graft, I frequently add a lateral extraarticular tenodesis (LET), a small additional procedure on the outside of the knee that adds rotational control and substantially lowers the re-tear risk. There is more on that in the questions below or on the dedicated lateral extraarticular tenodesis information page.
The surgery itself takes about an hour for an isolated ACL reconstruction, and up to two hours if a meniscus repair or LET is added. It is done under spinal or general anesthesia with a nerve block to control pain afterward. This is an outpatient surgery at the Proliance Surgery Center at Valley, and you go home the same day. As with any surgery, there are risks: stiffness, infection, blood clots, numbness around the incisions, lingering pain and swelling, and re-injury to the graft. We work together throughout the recovery to keep those risks as low as possible.
How a Meniscus Repair Changes Your Recovery
A meniscus tear is the most common injury I find alongside an ACL tear, and when the tissue is healthy enough to hold stitches, I repair it during the same surgery. Preserving the meniscus protects the knee from arthritis down the road and helps stabilize the new ACL graft. The tradeoff is that a stitched meniscus heals slowly and has to be protected, so the early recovery becomes more conservative than for an ACL reconstruction alone. For a standard meniscus repair, you can put weight on the leg right away but will use crutches for about four to six weeks, wear a hinged brace for six weeks that limits bending to 90 degrees, and avoid squats, lunges, or any loaded bending past 90 degrees for five months. Running moves out to around month five, not before. Learn more about meniscus repairs.
For a meniscus root repair or a radial tear repair, the restrictions are stricter, because those tear patterns cannot be loaded early. You will be completely non-weight-bearing on crutches for six weeks, in the brace for at least six weeks and then weaned off it as you start walking, usually by eight to ten weeks, and under the same five-month limit on deep bending, with walking unassisted around ten to twelve weeks. In every case the meniscus restrictions lift by month five and return to cutting and pivoting sports happens after nine months once you pass a return-to-sport evaluation with your physical therapist. The meniscus repair slows the first half of the recovery, not the finish line, and I will confirm which pathway you are on right after surgery.
ACL Recovery Timeline
Drag the slider or select the post-operative time to explore each phase of your recovery
Surgery & Physical Therapy Resources
Discover detailed instructions and protocols to guide patients through Pre-Op, Post-Op and Physical Therapy from Dr. Merritt.
Related Articles
Read more from Dr. Merritt about ACL tears, reconstruction, and recovery.
Common ACL Tears and Reconstruction Questions
Injury Information
A: Yes! This is a great question and on the forefront of current discussion and treatment. In high risk patients (young, hypermobile, significant instability) or a revision ACL, we almost always do an LET along with the ACL reconstruction. This surgery involves adding extra support to the outer side of the knee with a strip of the IT band to prevent the rotational movement that causes ACL tears. Studies have shown a significant reduction in ACL retears when this procedure is added to the standard ACL reconstruction.
A: You should see an orthopedic provider and get a full work-up that includes an MRI. Many times a year I see a patient who has injured their knee in a classic “ACL tear” mechanism but has been told it is just a sprain. They do PT and eventually the swelling goes down, but the knee still feels loose when trying to twist or pivot. Unfortunately, this instability is causing additional damage to the cartilage and meniscus and, over time, compounds the injury and leads to additional injuries in the knee. It is important to be your own health advocate. If your knee does not feel right, come see a provider who specializes in knee injuries. My team and I are happy to see you.
A: In most patients the knee will remain unstable, and cutting, pivoting, and twisting will continue to be painful and feel unstable. This additional and unnatural instability in the knee puts stress on the meniscus and shear forces on the cartilage. Many studies have demonstrated that these additional forces lead to much higher risks of meniscus and cartilage damage in the knee.
A: Not all ACL injuries need surgical treatment. In low demand patients or older patients, surgery can be avoided. In some cases, older patients have partial tears or sometimes tears that are lower energy and can actually heal, but this is actually rare. In younger patients and those that desire to return to rotational, cutting, or pivoting sports, then generally ACL reconstruction is needed and leads to far better results. Young athletes tear their ACL with more energy and it is very rare that they heal on their own.
A: Having a traumatic injury to the knee does have long-term consequences, including arthritis. Even with treatment, there is a higher risk of developing “wear-and-tear” arthritis when you get older and a higher risk of cartilage and meniscus tears. Stabilizing the knee with an ACL reconstruction is protective of these problems and improves the long-term results over non-operative treatment. This means that, although reconstructing the ACL does not eliminate risks later in life, having a stable knee is far superior to an unstable knee without a reconstruction. I discussed this in detail in one of the videos above.
A: I have trained with some of the best, world-renowned surgeons. I have tailored my surgical practice around knee and hip surgery so that I can focus on the advanced and cutting-edge treatments for athletes of all ages and all competition levels. Additionally, my philosophy as a surgeon is to not only perfect my surgical skills and techniques, but also educate patients and families on the injury. I believe that the surgical reconstruction is one important part of the injury and recovery, but it is also important to be a teammate on the pathway to recovery. I am so honored to get to be involved with patients and walk them through the dark times and see them get back to sports and life! I feel this approach shines through when patients write testimonials about their experience and I encourage you to read through them below.
A: On average, I do about 100 ACL surgeries per year. Combined with meniscus and cartilage treatments of the knee, ACL injuries are one of the most common injuries I treat. I am a knee surgeon who specializes in the treatment of sports related injuries of the knee. My patients are generally athletic and young and desire getting back to pivoting sports. This is a very comfortable surgery for me.
A: Get seen by a qualified orthopedic surgeon or orthopedic clinic ASAP. The most common presentation for an ACL injury is a buckling sensation, often associated with a pop in the knee, and then subsequent swelling. This injury is best addressed quickly. Early treatment and appropriate diagnosis are needed to expedite recovery. An MRI is needed to fully diagnose the injury and can help lead early rehabilitation and better surgery and recovery. If you’re having these symptoms, call us or be seen in our urgent care promptly so that we can quickly get you on the road to recovery.
A: Take a breath. This is a serious injury, but it’s also one of the most well-understood and successfully treated injuries in sports medicine. We got this! First, get seen as soon as possible. In the meantime, learn all you can on this webpage, watch the videos to get informed, and read my “Parent Guide to ACL Injuries” to better understand what is to come.
A: Reconstruction is the replacement of torn tissue with new tissue called a graft. Repair of the ACL keeps and repairs the torn ACL fibers natively in the knee. Repair of the ACL has gained attention in the last few years. This is a complex conversation and is only applicable to specific types of ACL tears—and is something that we can discuss in detail in the clinic.
Surgery Information
A: There is no “best graft” for an ACL reconstruction. I aim to offer all graft options and tailor the selection to each individual patient based on their needs, occupation, risk factors, and injury pattern. This is not a “one size fits all” period. A large part of our conversation in the clinic prior to surgery is the discussion of graft options, and an overview can be found in the video above. I perform bone–patellar tendon–bone (BTB) autograft, hamstring autograft, quadriceps tendon autograft, and allograft options and tailor the best graft option for each individual patient.
A: Studies suggest 4-8 weeks after injury is a good time for surgical treatment. After an injury, it is common for the knee to get stiff and lose range of motion. For this reason, we often do pre-surgical rehabilitation with physical therapy. Surgery is delayed until you restore full range of motion and have good quad control. This gives time to decrease the initial trauma and inflammation from the injury, so that recovery from surgery is faster and long-term issues like stiffness and poor quadriceps function are prevented.
A: ACL surgery is performed under spinal or general anesthesia with a nerve block to help with postoperative pain control.
A: ACL reconstruction and ACL repair surgery generally takes one hour. This is extended if additional surgery needs to be performed such as meniscus tears or additional ligament reconstruction or stabilization.
A:
- Verify check-in time and follow the instructions on when to stop eating and drinking
- You should have been prescribed Physical Therapy at the time of your clinic appointments before surgery. Make sure you have called and made an appointment with Physical Therapy for 5-7 days after surgery.
- Bring your brace that will be put on at the time of surgery
- Wear comfortable clothes that are easy to put on over a brace (sweatpants work well)
- No perfume or lotion on your skin
- Avoid jewelry or it will need to be removed before surgery
- If using an ice machine, make sure you have ice ready to be used at home
- It is recommended to have clean sheets in your bed and laundry done with clean and comfortable clothes
A: A couple of days before surgery you will receive a call from the nursing staff to explain your check-in time and when to stop eating and drinking. On the day of surgery, remember to bring your brace to surgery. Check in at the front desk of our surgery center at the time you were told. You do not need to arrive earlier. The friendly front desk staff will verify your name and the procedure and have you sign some documents related to getting surgery. You will then be brought back to the “Pre-Op” area with your family where our skilled nurses will help you get changed, shave your leg, start an IV, and go over your medications, allergies, and health history. You will meet with me before surgery and I will review the surgery and together we will identify the correct procedure and knee being treated. Anesthesia will meet with you and review the planned anesthesia. When the operating room is ready, you will say goodbye to your family and walk back to the operating room with one of our nurses. The nurse will introduce you to everyone in the room and you will lie down on the operating room table. Anesthesia will be given and you will not remember anything until you are in the recovery room.
While in surgery, your family will pick up your post-operative medications at the pharmacy next to the Surgery Center. If you are under 18, one family member needs to stay at the surgery center for the entire surgery. In this case, medications can be picked up on your way out.
In the recovery room you will be monitored by the nurses until you are awake and stable and then be transferred to a room where you can again be with your family. You will have some crackers and juice or soda and they will make sure you are comfortable and give you pain medications as needed. Once you feel ready, you will change into your street clothes and be wheeled to your car.
A: Yes, this is a covered procedure by insurance programs. The cost varies by insurance plan and your deductible status. We will give you a very accurate summary of what to expect before surgery.
Post-Op Recovery
A: This is a major surgery in that you will need anesthesia and will have a team of professionals in an operating room to help you through surgery. There will be some pain associated with having surgery, but the most common response I receive from patients is that they expected it to hurt more. Different graft options have different pain levels, but in general this is not considered an overly painful operation.
A: Yes, you will be in a brace to protect the reconstruction and allow walking while the quad muscles wake up from surgery. You will be prescribed a brace at your preoperative visit that will be worn until you have good control of your quadriceps to prevent any buckling as you start to weight bear. Depending on additional trauma or surgery that is done, this brace may need to be on for six weeks or longer, but if an isolated ACL surgery, the brace often comes off around 3 to 4 weeks, once you are off crutches with good quad control. We generally recommend getting into physical therapy within the first week after the surgery to start working on range of motion, activation of your quadriceps, and mobility, including walking.
A: If you have just had an ACL reconstruction, then yes you can remove the brace for sleeping. If we also performed a meniscus repair, then you need to sleep with the brace on to prevent deep flexion while you sleep.
A: 2-6 weeks depending on how quick you regain strength and any additional surgery to the meniscus that was needed. If you also require repair of the meniscus, the brace will be worn for 6 weeks.
A: Early after surgery, this is more common than not. You will have bleeding, swelling, and some scar tissue that forms and then resolves over time. Additionally, this is also common to feel when transitioning to more athletics around the 5 month mark because the knee again goes through a period of adjustment to the new activity. Long term, some clicking can remain if there has been some cartilage injury with the ACL. Generally, most clicking resolves during the post-op recovery timeframe.
A: Surgery causes some bleeding and it is frequent that this bleeding drains down the leg after surgery. This is minimized by icing and elevation. It is normal for the lower leg and ankle to have some bruising and this alone is not a sign of a problem. Bruising by itself is not a sign of a blood clot, but call us right away if you have calf pain or tightness, increasing swelling in one leg, warmth, or shortness of breath.
A: Yes. The surgery is done with fluid to see into the knee and this fluid will often leak out for a few days after surgery. Sometimes the incisions will also have some bleeding. This is normal. If there is excessive bleeding or draining down the leg, please give us a call.
A: Yes to both. After surgery you will have swelling and pain in the knee. Swelling causes more pain and makes regaining range of motion more difficult. For these reasons we recommend the use of an ice machine and elevation of the knee after surgery. The first couple of weeks are all about pain control, decreasing the swelling, getting into physical therapy, and gentle range of motion.
A: You can shower 48 hours after surgery. At this time the ACE wrap is removed and you can shower.
A: Physical Therapy is very important in ACL recovery. Initially they will work on getting the knee fully straight. Extension is a critical early milestone in recovery. They will also work within our restrictions to get flexion (knee bend) and the muscles of the lower leg active. It is common after ACL surgery to have weakness and sluggish quadriceps and they will use strengthening techniques and modalities like E-stim and blood-flow restriction to get the muscles to wake up. This is critical for walking, progressing off the crutches and out of the brace. Over the full recovery, they will work on transition to jogging and running, sport-specific drills, and ACL prevention of both the injured and non-injured leg.
A: General timeframes are:
- Driving if right leg surgery: 4-6 weeks and off narcotic medications
- Driving if left leg surgery: 2-4 weeks and off narcotic medications
- School: 1-2 weeks
- Work: Depends on your job. Sedentary job within a week or two. Jobs that require cutting and pivoting may take the whole 9 months (ex. ski patrol and police officer)
- Running: 3-5 months depending on additional meniscus surgery
- Sports: 9-12 months for cutting and pivoting sports
A:
Driving if right leg surgery: 4-6 weeks and off narcotic medications
Driving if left leg surgery: 2-4 weeks and off narcotic medications
A: Most people are able to start working out again in the first week after surgery. You will be working out with physical therapy to start activating your quadriceps and working on range of motion. Core and upper extremity workouts can be done as soon as you are comfortable. The progression to full sports is generally nine months, but in the time period between surgery and full sports, you will be working out and still very active. I discussed this more in one of the videos above.
A: 9 months is when sports surgeons allow patients to return to cutting and pivoting sports provided the body and muscle strength is ready for those sports. There is nothing magical about this timeframe and it is more used as a “biological timeframe” for when we feel the graft is strong enough to withstand pivoting activities. In truth, the graft continues to “mature” and strengthen for 2 full years after surgery. If accelerated return to sports is not an important goal of the patient, I often recommend delaying for 12-18 months to lower the risk of retear. Please see my ACL Rehab and Results Video for more detail.
A: Yes, a good diet and increased protein and collagen supplementation can speed recovery and prevent muscle weakness after surgery. Please see my nutrition page for more details. Protein supplementation helps muscle growth and avoids atrophy. Collagen supplements provide the body with the building blocks for cartilage and ligament regeneration. Additionally, Vitamin C can help with inflammation and stiffness in the surgical time period. These are best started prior to surgery and continued through the recovery. Other supplements do not have any compelling data for use. Many patients take supplements, but some should be stopped before surgery, so please tell us everything you take.
A: Everyone that has an ACL tear is at increased risk of “post-traumatic” arthritis in the future. This is an unavoidable consequence of the trauma of the initial injury. Reconstructing and stabilizing the knee decreases the risk of further damage to the knee but does not eliminate the risk. The best way to minimize the long-term risk is to stay healthy, keep your body weight down, avoid smoking and nicotine products, and stay strong and flexible around the knee. Some studies suggest running and sustained impact athletics increase the risk of arthritis on a previously injured knee.
A: This is complicated and there is no single answer. This depends on risk factors for tearing the ACL, additional injuries or reconstructions at the time of surgery, compliance with PT and return-to-sport timeframes, graft used for reconstruction, and a million other factors. In general, in active patients returning to cutting and pivoting sports, the risk is often quoted at about 10 to 15%. Interestingly, the risk of tearing the other, uninjured ACL is about the same and, in many studies, is actually higher. This means that, while we can’t eliminate the risk of retear completely, we make the risk about the same as the side without the ACL reconstruction.
See what other patients say about their experience.
You deserve to move freely again. We will help you take that step.
Call to book an appointment
(425) 291-1496