
Cartilage Repair: OCD and Fragment Fixation
Cartilage repair saves a damaged piece of a person’s own cartilage and bone and fixes it back in place, the way a fracture is fixed. It is used for osteochondritis dissecans (OCD) and for fragments knocked loose by an injury. Cartilage is the smooth layer that covers the ends of the bones in the knee. It has no blood supply, so it cannot heal on its own, but a fragment that still has healthy bone attached to it can heal back to the bone underneath.
An OCD is an injury to the knee where a piece of bone and cartilage fails to fully fuse to the rest of the knee. This often leaves an unstable fragment of cartilage and bone, most commonly on the inner side of the end of the thigh bone (the medial femoral condyle). It is usually seen in younger patients who are physically active. If the OCD lesion remains stable, often nothing needs to be done, or I can stimulate healing with retrograde drilling. If the fragment becomes unstable but the cartilage and bone are still good quality, I can repair it with fixation, like a fracture.
The trauma of a kneecap dislocation can also knock off a piece of cartilage, either from the kneecap or from the outer side of the groove it runs in (the lateral trochlea). If this is seen on an X-ray or MRI, I try to address it quickly, to prevent the fragment from breaking apart and to fix the injury while there is still good healing potential. On the kneecap, the cartilage injury is often small and does not need treatment. If the fragment is large and on the outer side of the knee, fixing it urgently is important.
Patients with an OCD or a loose fragment usually describe pain with activity, swelling, and sometimes catching, locking, or the feeling that something is moving around in the knee. X-rays can show an OCD or a fragment with bone on it, and an MRI shows whether the fragment is stable and how healthy the cartilage is.

Video Education
Dr. Merritt has developed an in-depth video on Advanced Cartilage Treatment Surgery Information. This video helps patients understand the condition, the procedure, and what to expect.
Treatment Options
Usually, by the time I see a patient for an OCD, it has become unstable. Once it is unstable, there is no healing capacity, and we need to stabilize it to try to save the bone and cartilage. If the lesion is stable and the patient has open growth plates, the goal is to protect the knee and limit physical activity to give the fragment a chance to heal. We assess the stability of the fragment on MRI by looking for joint fluid that has gotten in between the fragment and the underlying bone. I usually give the fragment 6 months to show signs of healing.
For a stable lesion with open growth plates, I often treat this without surgery, with limited weight bearing, and the fragment has a high chance of healing. In one study of young patients with stable OCD lesions, about two-thirds showed healing after six months of activity changes and protection, and smaller lesions were more likely to heal.
With closed growth plates, or if I am concerned that the fragment is about to become unstable, I often do retrograde drilling. In retrograde drilling, I drill into the fragment through the bone underneath it. This makes the body treat the area like a fracture and builds a connection between the underlying bone and the fragment so that it heals. If the fragment is unstable and joint fluid has gotten between the OCD lesion and the underlying bone, healing becomes less reliable, and I usually recommend surgical fixation.
In this surgery, I lift up the fragment, clean out any tissue between the fragment and the underlying bone, and get down to good, bleeding bone that can heal, adding bone graft when bone is missing. I then hold the fragment in place with headless compression screws, which sit below the cartilage surface and do not need to be removed.
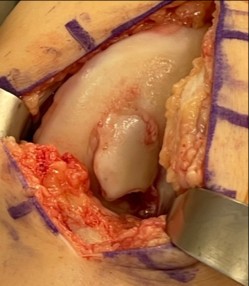


The same repair works for a piece of cartilage and bone knocked off by a kneecap dislocation. In the case below, the fragment came off the outer side of the end of the thigh bone during a dislocation, and I used sutures over the top as well as screws to hold the large fragment flat.
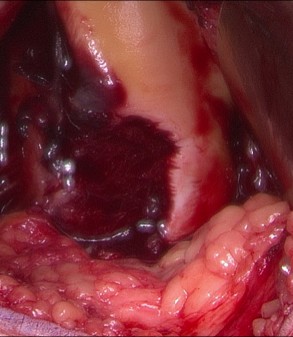

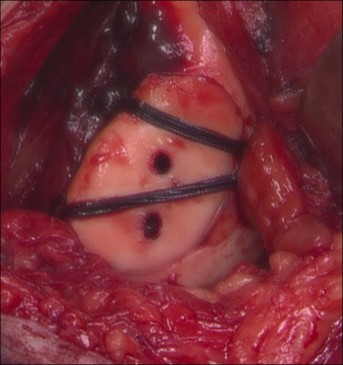
I decide whether a fragment is worth saving based on the quality of its bone and cartilage. If the fragment has broken into many pieces, or the cartilage on top has worn away, the better option is usually an osteochondral allograft. For a contained cartilage defect with healthy bone underneath, MACI is another option.
Fixation can also be combined with an alignment procedure such as a tibial tubercle osteotomy (TTO) when the kneecap tracks off-center, or an osteotomy of the shin bone or thigh bone when the leg’s alignment overloads that side of the knee.
Recovery and Results
Restrictions after OCD fixation depend a lot on the location of the injury. Sometimes I limit weight bearing if I think that putting weight on the leg will stress the fragment while it is trying to heal. Other times, I limit deep bending. When the fixation is combined with an alignment procedure such as a tibial tubercle osteotomy, the recovery follows that procedure’s protocol. The screws are headless compression screws and generally do not need to be removed. The plan below is for fixation on the end of the thigh bone (femoral condyle), which follows the same path as an osteochondral allograft there, since in both cases we are waiting for bone to heal to bone.
The first two weeks
Weeks 0 to 2
Most of this stage is about protecting the fragment, controlling swelling, and keeping the knee straight.
- Weight bearing: Toe-touch only (about 10 to 15 pounds, for balance), with crutches for every step, even when the knee feels good.
- Brace: Hinged and unlocked for walking from day 1. Take it off for sleep, bending exercises, and showering.
- Swelling: Ice 20 minutes on and 20 minutes off, keep the leg up, and rest with a pillow under the calf, never under the knee. Pain and swelling peak around days 2 and 3.
- Exercises: Quad sets and ankle pumps every waking hour, straight-leg raises, and gentle bending with the brace off. The goal is 90° by 2 weeks, without forcing it. No CPM machine is needed.
- Therapy: Physical therapy starts 5 to 7 days after surgery, 2 times a week, with electrical stimulation to wake up the quadriceps.
- Medicines: Aspirin 81 mg twice a day for 6 weeks to lower the risk of blood clots, and no anti-inflammatory medicines. Tylenol on a schedule for the first 2 weeks; most people are off narcotics within 1 to 2 weeks.
- Milestones: Showering starts at 48 hours with the incisions covered, and the stitches dissolve on their own. Your 2-week visit checks the incisions and your motion. Desk work or school is often possible around 2 weeks if you can keep the leg up.
Protect the fragment
Weeks 2 to 6
You are still toe-touch weight bearing on crutches while the fragment starts to heal to the bone underneath.
- Motion: Keep building your bending. The stationary bike starts once you reach about 100°, usually at 4 to 6 weeks.
- Exercises: Straight-leg raises in all directions, hamstring curls, and hip and calf work, all while sitting or lying down.
- Pool: Pool walking at 4 to 5 weeks once the incisions have healed and I have cleared it. No baths, pools, or hot tubs before 4 weeks.
- Avoid: No standing exercises, squats, or lunges, and no partial weight on the leg before week 7.
Adding weight
Weeks 7 to 12
Weight is added once your quadriceps control is good.
- Crutches: Two crutches, then one, then none, usually by 8 to 10 weeks.
- Brace: Stops once you are off crutches with good quadriceps control.
- Medicines: Aspirin stops at 6 weeks, and we talk about restarting anti-inflammatories.
- Exercises: Weight shifts, light leg extensions, mini squats (to 60°, then 90° by week 12), leg press, 4 to 6 inch step-ups, calf raises, and balance work. The elliptical starts once you are off crutches.
- Avoid: No running, jumping, or impact.
Strength and running
Weeks 13 to 16
Strengthening gets harder and impact starts gradually.
- Exercises: Deeper squats, single-leg leg press, step-downs from 4 up to 8 inches, and balance board work.
- Plyometrics: Two-leg jump-and-land drills from weeks 13 to 14, building to single-leg hops, plus light agility work like ladders and side shuffles.
- Running: Running on flat ground usually starts at 14 to 16 weeks, once you pass the 8-inch step-down test with good mechanics.
- Goal: Quadriceps strength at least 80% of the other leg.
Return to sport
Months 4 to 6
Sport-specific training builds toward a full return once the fragment has healed on X-ray or MRI.
- Running: Walk-jog intervals building to continuous running, adding distance before pace.
- Cutting: Cutting, jumping, and agility drills start no earlier than about 5 months (22 weeks), then sport-specific training.
- Testing: Strength testing and single, triple, crossover, and timed hop tests.
- Return to sport: Usually after 6 months, once quadriceps strength and hop tests are at least 90% of the other leg, you can run 20 minutes without pain or swelling, and I have cleared you.
These injuries are often the aftermath of a big injury to the knee. As with any big injury, I am trying to keep as much of your own tissue as possible and restore the knee to as close to normal as possible. By saving the cartilage fragment or fixing the OCD, we are hoping to restore the normal cartilage surfaces of the knee, and this often produces excellent results. If the fixation fails for some reason, an osteochondral allograft is generally the next step.
In a review of internal fixation for unstable OCD lesions in adults and older teenagers, the rate of healing on X-ray ranged from 67% to 100% across studies.
Surgery & Physical Therapy Resources
Discover detailed instructions and protocols to guide patients through Pre-Op, Post-Op and Physical Therapy from Dr. Merritt.
Related Articles
Read more from Dr. Merritt about kneecap dislocations and cartilage repair.
Common OCD and Fragment Fixation Questions
Injury Information
A: When a dislocation knocks off a piece of cartilage and bone, the fragment can break apart and its healing potential drops over time. Fixing it quickly gives the best chance of saving your own cartilage.
A: On MRI, I look for joint fluid that has gotten in between the fragment and the bone underneath. Fluid behind the fragment means it has separated and is unlikely to heal on its own. Symptoms such as catching and locking also point toward an unstable fragment.
A: No. Stable lesions in young patients with open growth plates often heal with rest, activity changes, and limited weight bearing. Surgery is needed when the lesion is unstable, has not healed after a period of protection, or when the growth plates have closed.
A: The exact cause is not fully known. Repetitive stress from sports is thought to play a large role, which is why it is most common in young, active athletes. It is not caused by a single injury the way a fracture is.
A: OCD is a condition where a piece of bone and the cartilage on top of it does not fully fuse to the rest of the bone. Over time the piece can loosen and become unstable. It most often affects the inner side of the end of the thigh bone in active children and teenagers, although it can show up in adults.
Surgery Information
A: If the fragment is broken into many pieces or the cartilage on it is worn out, I usually recommend an osteochondral allograft, which replaces the damaged cartilage and bone with a matched donor graft. If the fixation fails later, an allograft is generally the next step.
A: Usually not. I use headless compression screws that sit below the cartilage surface, so they do not rub on the joint and generally do not need to be removed.
A: Retrograde drilling is a small surgery where I drill into the fragment from the bone side, without going through the cartilage surface. This brings new blood supply to the area and makes the body treat it like a fracture, so the fragment heals to the bone underneath.
Post-Op Recovery
A: It depends on where the lesion is and how it was treated. After fixation, impact, cutting, and pivoting activities usually start at about 5 months, with a full return to sports at around 6 months. Sports resume only after the fragment has healed on X-ray or MRI and strength and motion have returned.
Studies Cited
- Wall EJ, Vourazeris J, Myer GD, et al. The Healing Potential of Stable Juvenile Osteochondritis Dissecans Knee Lesions. J Bone Joint Surg Am. 2008. PubMed
- Leland DP, Bernard CD, Camp CL, et al. Does Internal Fixation for Unstable Osteochondritis Dissecans of the Skeletally Mature Knee Work? A Systematic Review. Arthroscopy. 2019. PubMed
See what other patients say about their experience.
You deserve to move freely again. We will help you take that step.
Call to book an appointment
(425) 291-1496